We make clinical AI safer and easier to monitor.So you can catch problems early and act with confidence.
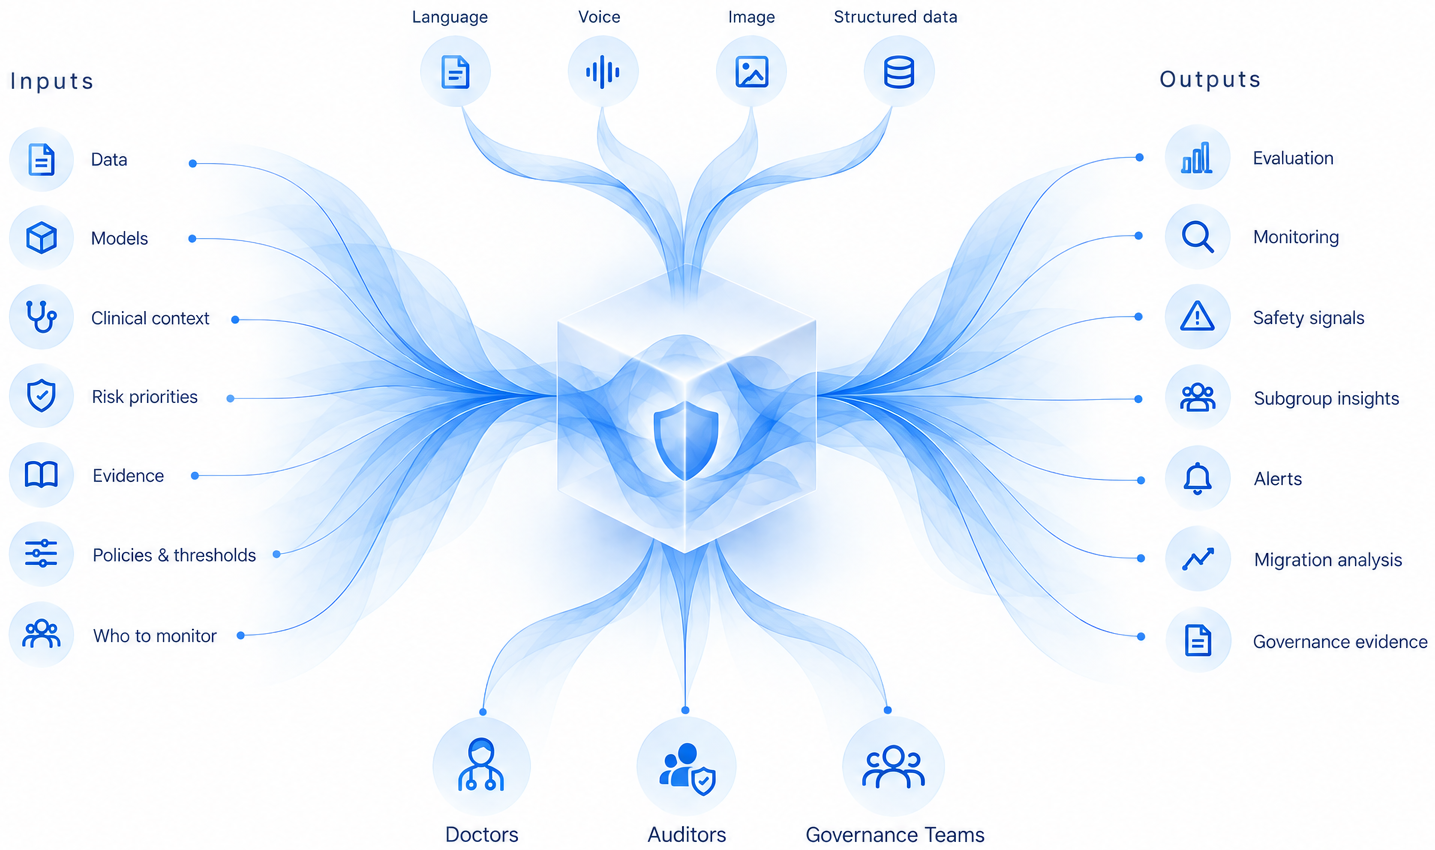
From guesswork to continuous assurance.

AI gets tested once before deployment.

Quality gets judged by vibe checks.

Generic benchmarks define AI quality.

Safety failures can go unnoticed.

Evaluations aren't tailored to workflows.

Model providers become trusted sources.

Subgroup performance remains largely invisible.

Production changes rarely trigger re-evaluation.

AI gets continuously evaluated in production.

Quality reflects real-world clinical performance.

Hospitals define their own evaluations.

Safety-critical failures get actively monitored.

Models are tested across specific subgroups.

Independent engines verify evaluation evidence.

Drift and degradation trigger investigation.

Every decision creates an audit trail.
AI failures are already clinical failures.
During a sinus procedure, the AI-assisted navigation system allegedly provided incorrect information about the location of surgical instruments. The patient suffered a carotid-artery injury and stroke; the manufacturer disputed that the system caused the injury.
A sepsis-alert system flagged a dialysis patient and prompted treatment toward aggressive IV-fluid administration. A nurse recognised the risk of fluid overload and prevented the recommendation from causing harm.
A chatbot reportedly suggested sodium bromide could replace sodium chloride. The patient followed the advice, developed severe bromism and psychosis, and required a prolonged hospitalisation.
A kidney-transplant patient reportedly followed chatbot advice and stopped prescribed transplant medication without medical supervision, and subsequently experienced graft failure.
An algorithm used to identify patients for additional support systematically underestimated the needs of Black patients, because it used healthcare spending as a proxy for healthcare need.
A sepsis prediction model generated many inaccurate alerts while missing a substantial proportion of patients who developed sepsis — alert fatigue alongside missed deterioration.












 Evaluate
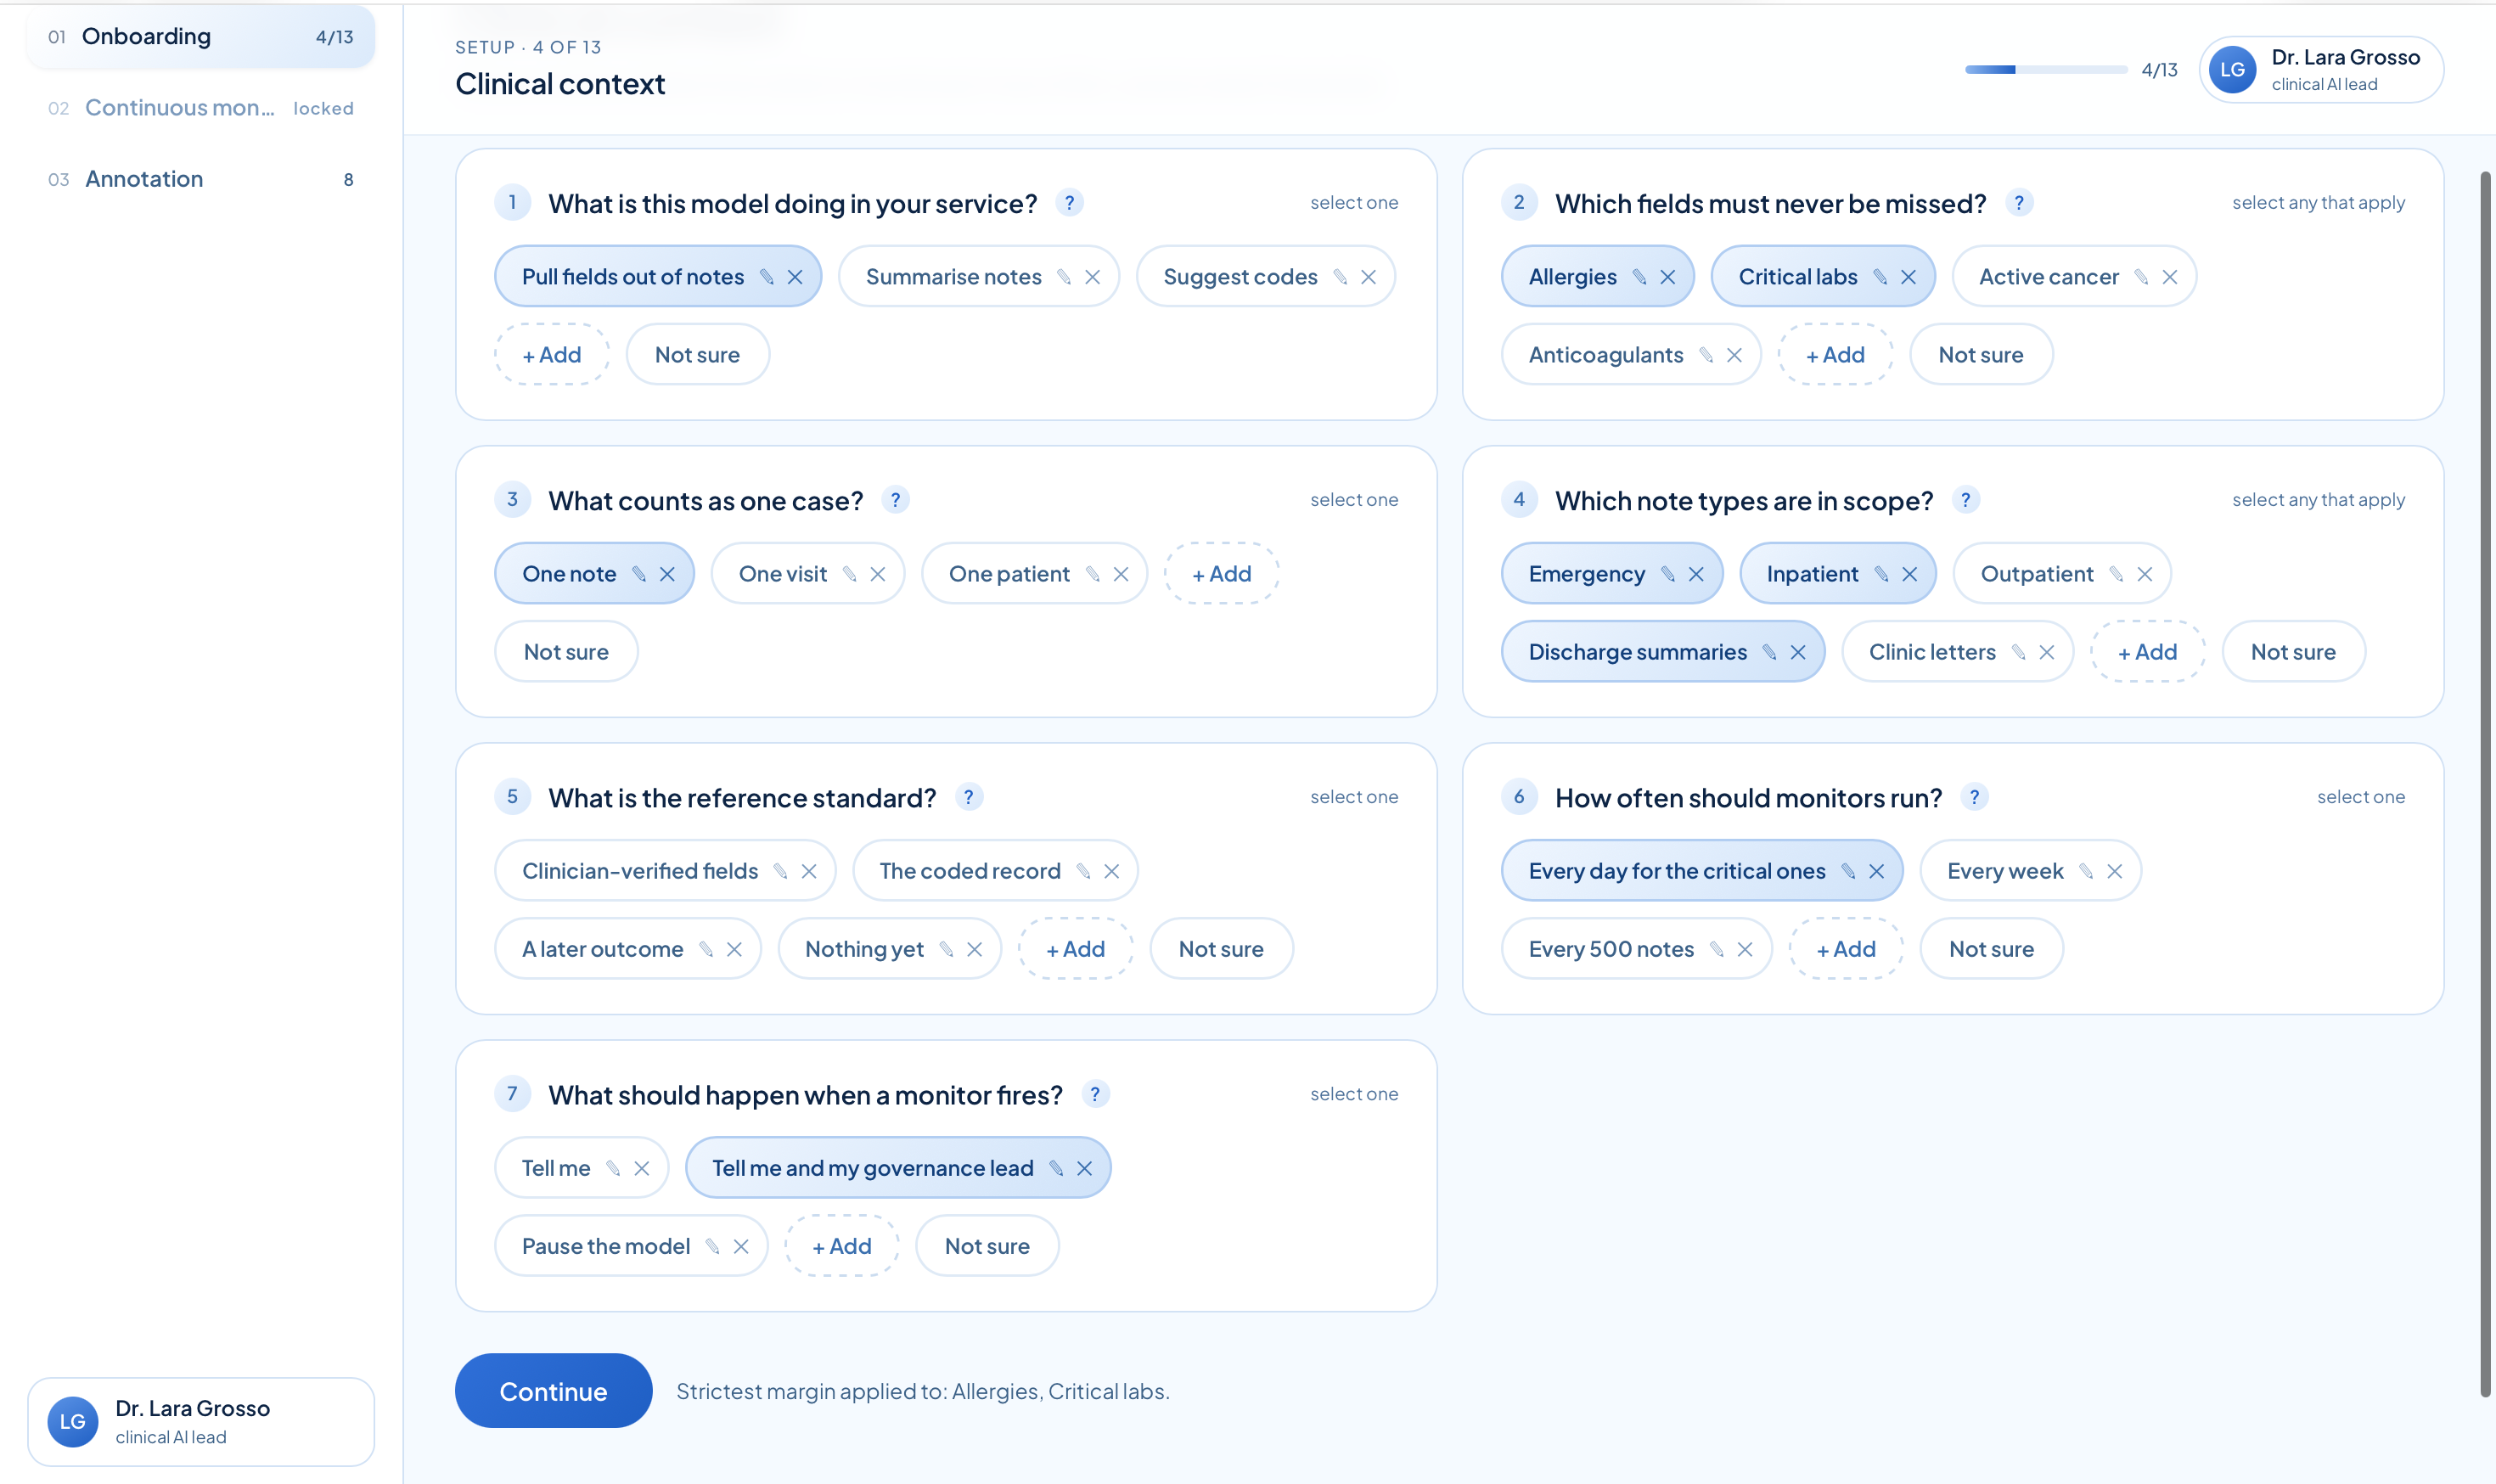
Your clinical teams decide what matters.
The people closest to care define what safe evaluation looks like.
SafeAI turns that expertise into a repeatable evaluation system.



Create private, institution-specific evaluation datasets and challenge sets that reflect how your teams actually work.



 Monitor
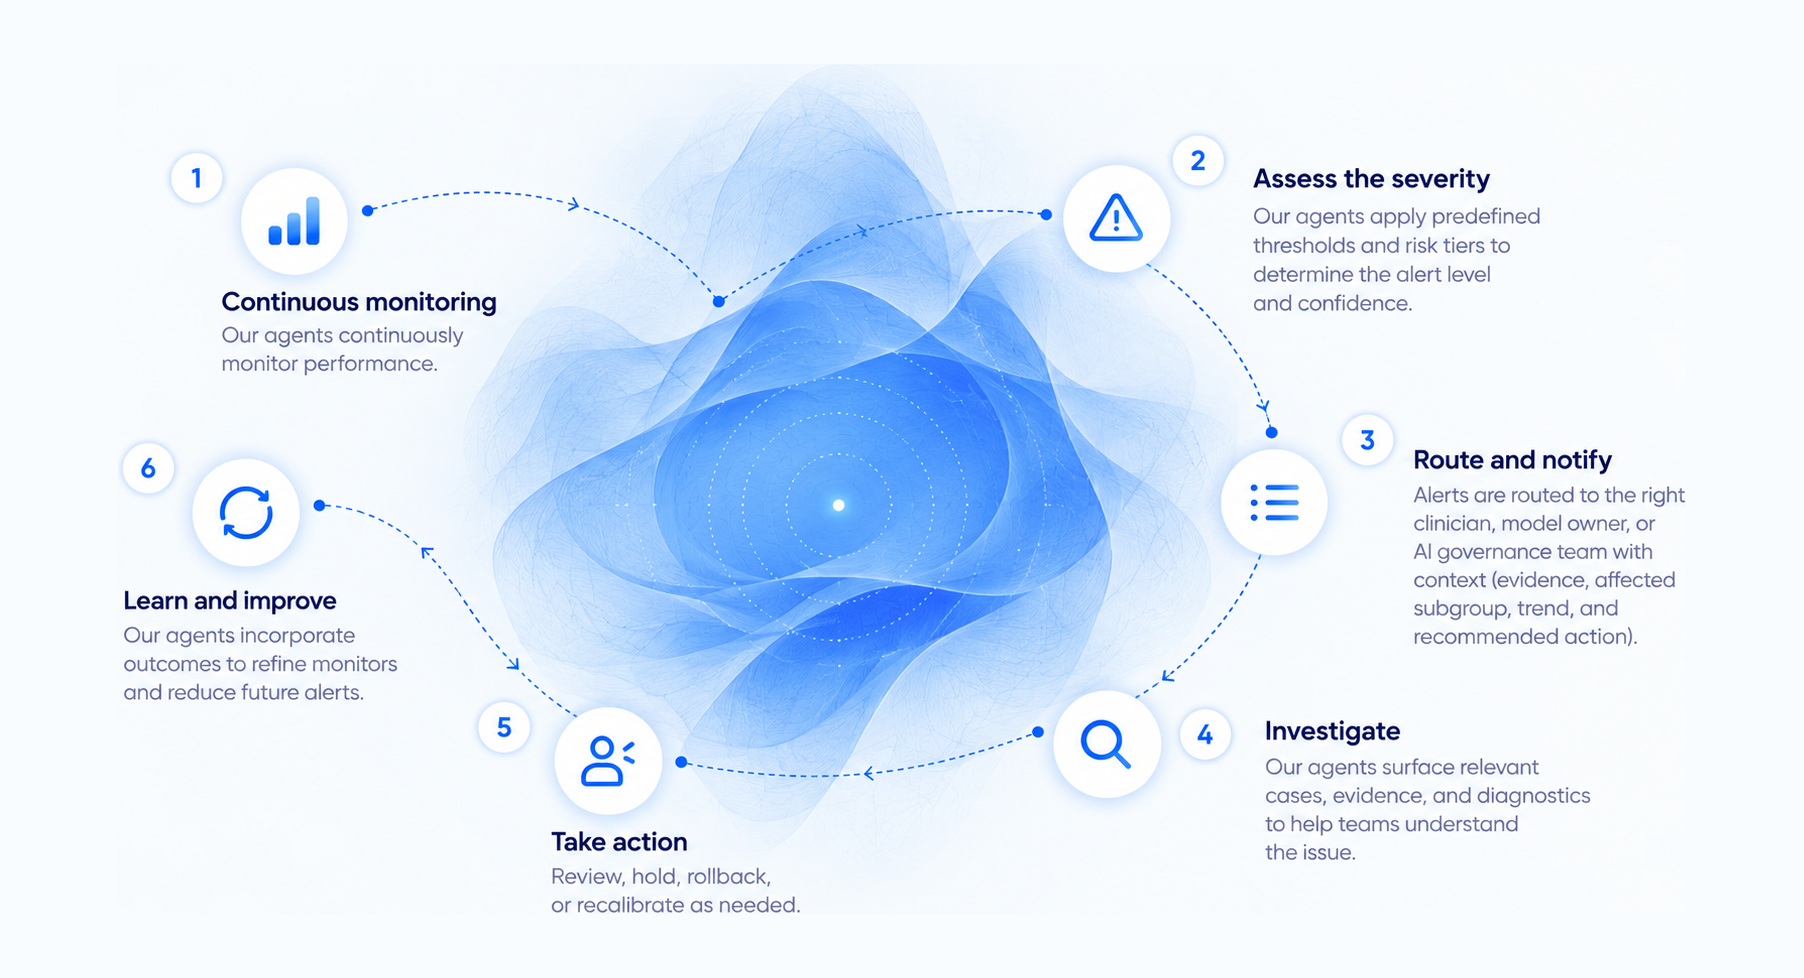
Six families of monitors.
First we evaluate and set a baseline. Then our agents continuously monitor it, as per the guidelines you set.





 Alerts
When something changes, do you know whether it matters?
 Team
Clinical safety is a multidisciplinary problem.
Clinicians, AI safety researchers, statisticians, engineers, governance leaders and product builders working on one problem: making clinical AI oversight scalable.
Core team

Lara Grosso
Harvard DrPH and SafeAI Founder
DrPH at Harvard in AI & patient safety. 10+ years in global health (World Health Organization, CHAI) across 7 countries.
LinkedIn →
Luke Payyapilli
Seasoned software engineering leader with a track record of scaling systems and guiding technical direction, particularly in cloud infrastructure. Has led product-driven engineering initiatives at multiple successfully acquired companies, collaborating with stakeholders to deliver meaningful outcomes for these organizations and their end users.
LinkedIn →
Francesca Mussa
Harvard PhD and Statistician
PhD, AIM Harvard–BGB. Statistician building clinically meaningful medical AI, grounded in physiology & patient care.
LinkedIn →
Tirtha Pani
AI Safety Engineer
AI Safety scientist building machine learning systems to improve outcomes for people with chronic disease.
LinkedIn →
Isabelle Schulte
Harvard MPH, Health Management
Head of Business Development. Leads business development, fundraising, hospital partnerships, and GTM strategy. 8+ years in healthcare operations and transformation.
LinkedIn →
Filippo Bargagna
AI Safety Scientist | Research Fellow @ UNIPI
Supports the technical development of the SafeAI platform and its alignment to the clinical workflow. Research Fellow on ML and Signal Processing at UNIPI.
LinkedIn →
Sanjana Patnam
AI Safety Engineer Intern
Researches clinical AI failure patterns and builds evaluation frameworks for SafeAI. Graduate student at Northeastern University in Data Analytics Engineering.
LinkedIn →
Tajvir Chahal
AI Safety Engineer Intern
Building bias/equity audits for SafeAI's clinical AI platform. Background in data analysis; studying Machine Intelligence at Northeastern, with a B.S. in Computer Science from Rutgers.
LinkedIn →
Jonathan Lee
Business Development and Fundraising Intern
Supporting the development of business operations and fundraising of SafeAI Health. Undergraduate student at Northeastern University majoring in Finance.
Clinical partners

Mayo Clinic
Clinical validation partner
Ranked the #1 hospital in the world by Newsweek for eight consecutive years and a perennial U.S. News & World Report Honor Roll hospital.

Humanitas AI
Applied clinical AI research
The AI Center of Humanitas Research Hospital, a leading Italian academic hospital network spanning 12 hospitals.
Advisors

Brian Anderson, MD
CEO & Co-Founder, Coalition for Health AI (CHAI)
A physician and digital health pioneer helping shape national standards for trustworthy, safe and effective AI in healthcare. Previously Chief Digital Health Physician at MITRE and head of Informatics and Network Medicine at athenahealth. Harvard Medical School graduate.

Tom Pollard
Research Scientist, MIT · Technical Director, PhysioNet
Technical Director of PhysioNet and a contributor to the landmark MIMIC clinical databases. Instructor in Biostatistics at Harvard T.H. Chan School of Public Health, with a PhD in computational modelling of patient physiology.

Cyrus Massoumi
Founder & CEO, Dr. B · Founder & Former CEO, Zocdoc
A healthcare entrepreneur and investor who founded Zocdoc and went on to build Dr. B. Founder and Managing Partner of humbition, and a Senior Advisor to Columbia University's Mailman School of Public Health.
 Recognition
Awards and accelerators.

See it on your own models and data.
Bring us a model, a dataset, or a production monitoring problem. We'll map the evidence, risk, failure modes, and oversight workflow.